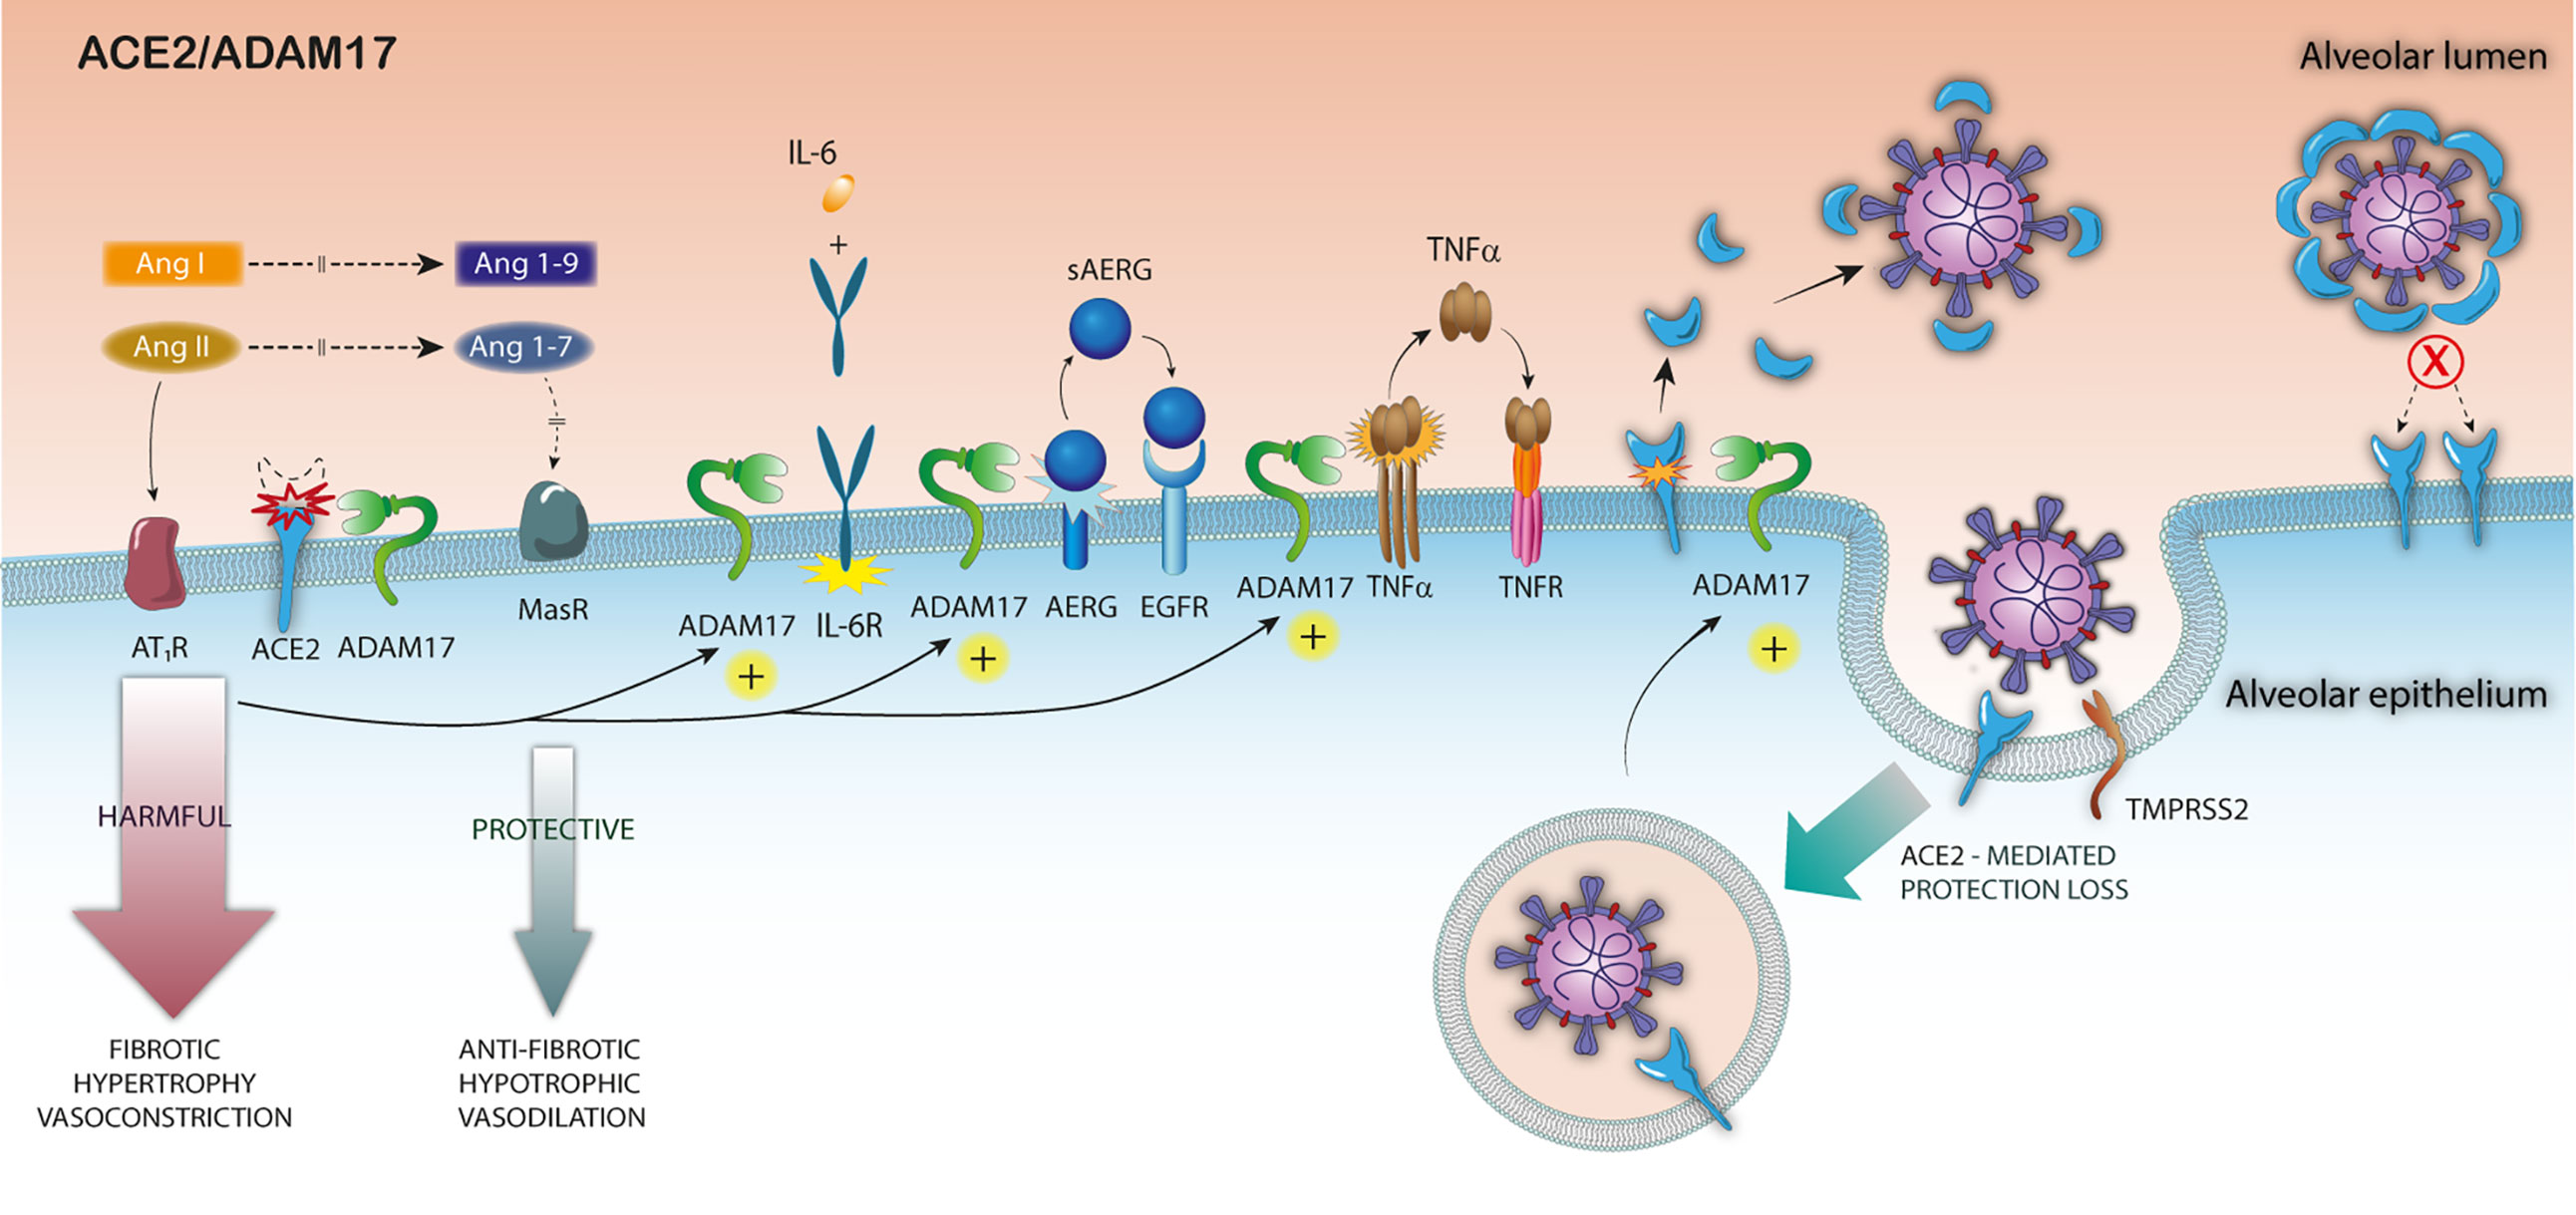
A diagram of the relationship between ACE-2 and ADAM-17, the unnamed sheddase in Dr. Klioze's video. Diagram from ACE2/ADAM17/TMPRSS2 Interplay article by Donato Zipeto et al.
Talk about an amazing closed-loop feedback system. And this is only HALF of the
closed loop. The part that tries to increase the blood pressure.
How ACE-2 figures into this
Done with RAAS, Dr. Klioz now concentrates on the ACE-2 protein found on the
outer membrane of certain cells in locations previously mentioned. Namely, the
GI tract, the lungs, the kidneys and blood vessels throughout our body.
Remember, the ACE-2 receptor is how the Covid-19 virus gets into our cells and
wreaks havoc. Dr. Klioz continued.
"3:25 The active form of ACE-2 (soluble ACE-2) is produced by an additional enzyme called Sheddase (Adam17). Sheddase (Adam17) cleaves the external component of the ACE-2 protein and
releases it into the bloodstream (as soluble ACE-2)."
We now know, thanks to Donato Zipeto et al that the Sheddase is in fact, ADAM17. That the cleaved ACE2 that was released into the bloodstream is called sACE2 or soluble ACE-2.
"3:36 The cleaved portion of ACE-2 interacts with Angiotensin-2, converting
it into Angiotensin 1-7.
Angiotensin 1-7 is a powerful antioxidant and vasodilator, dilating the
peripheral vessels of the body and eliminating the action of Angiotensin-2 on
the adrenals. Angiotensin 1-7 lowers blood pressure and is basically the
counter-balance to Renin-Angiotensin (Aldosterone) System."
Wow.
Recap: So low blood pressure triggers the Renin Angiotensin
Aldosterone System which constricts arteries throughout the body and has the
kidneys retain salt and water and expel potassium. To raise blood pressure.
When the body has had enough high blood pressure and wants it to go back down
to normal levels, something triggers the ADAM17 enzyme to
cleave a portion of the ACE-2 protein molecule away from itself and
sacrifice those pieces of ACE-2 to alter the workings of the Angiotensin-2
hormone, turning it into Angiotensin 1-7. Which does just the opposite, of what
Angiotensin-2 was doing. Angiotensin 1-7 lowers blood pressure by
dilating (or opening up) all constricted arteries and stops the Kidneys
from retaining salt and water by converting any free floating Angiotensin II into Ang I-7.
A true closed-loop feedback system. An elegant one at that. One that researchers and drug companies were able to exploit in order to stop hypertension or high blood pressure. If the body is sending out signals via the RAAS system to raise blood pressure via this pathway, researchers asked,
"What if we could short circuit the RAAS system that appears to be "out of control" and stop the message of "raise blood pressure" from getting all the way to end of this system (Angiotensin II binding to the AT1R receptor and vasoconstricting blood vessels) and ADAM17 (the quarterback of this system at the far end) doing all of it "harmful" processes? Would we be able to control High Blood Pressure?"
The answer was apparently yes, as a number of drugs that are on the market do exactly that - they get inside the RAAS system and stop the message (Angiotensin II) from getting all the way to the end of this feedback system, vasoconstricting blood vessels and instructing ADAM17 to start its harmful cycle.
"4:01 There are Medications that also counteract the effects of Renin - Angiotensin system, including Angiotensin Converting Enzyme Inhibitors (ACEI), and Angiotensin Receptor Blockers (ARB).
ACEIs are just like they sound, blocking Angiotensin Converting Enzyme from transforming Angiotensin I to Angiotensin II.
Angiotensin Receptor Blockers are also self descriptive, working a little further down the line, blocking Angiotensin II from binding to its receptors on the blood vessels and adrenal glands."
Now initially, I had left this part of Dr. Klioz's video out of my original post. This now being October 2021, I've added this in as another critical piece of the story. Dr. Klioz continued.
Hypertension Drugs and Covid-19
"4:37 During the early part of the pandemic, there was some concern that both ACEIs and ARBs could increase the risk of a viral infection by upregulating the expression of the ACE-2 surface proteins throughout the body. However preliminary data has shown just the opposite. Covid-19 patients on Angiotensin Converting Enzyme Inhibitors or Angiotensin Receptor Blockers do much better with decreased all-cause mortality if they stay on their blood pressure medications during their infection.
Whether this is due to lessening the impact of the infection itself, or simply preventing death from the complications of hypertension is currently not clear and more research is needed."
This is huge.
Why?
Simply because after pulling the hospital records on my mom's visit to emergency, I discovered that mom was taking Ramipril, an ACEI or Angiotensin Converting Enzyme Inhibitor.
Why is that huge?
I'll circle around to that in a second.
So why target the ACE-2 receptor?
Dr. Klioz goes on to postulate
the brilliance of the virus in targeting this specific receptor. As previously
mentioned, the ACE-2 receptor is found in 4 key waste elimination systems. The
lungs, the kidneys, the blood vessel walls and the GI tract. So, if it were to
infect say a lung cell, via the ACE-2 receptor, and get inside that lung cell
and replicate itself thousand fold (or more), upon leaving the lung cell it
would get coughed out and possibly spread to another host. Same for being
pooped out the GI tract, peed out the bladder or transmitted via
transference of blood. It is highly infectious and great at spreading
itself around.
Then he turns to the meat of our discussion.
How and possibly why Covid-19 is
successful in some people and not others
"7:18 The clinical response to a Covid-19 infection likely depends on three
dominant factors. The initial viral load, the integrity and strength of your
immune system and number and configuration of the ACE-2 surface proteins that
serve as a portal of entry for the viral particles"
Says Dr. Klioz. We've been told about all these things in different ways.
Update October 2026:
A positive PCR test means the virus's genetic material (its RNA) was found in your nose or throat. That usually means the virus is already replicating there. How sick you get from that point depends on several factors:
1. Initial viral loadHow many viruses did you get in one shot? Did you share a bottle of water with
someone who had Covid-19? Or did you simply walk past someone who breathed it
out? Were you in close proximity to a loved one, who might be asymptomatic for
long stretches of time? Or did you touch that carboard box that just arrived via mail?
The New England Journal of Medicine did a study on how long Cov2 can exist on different surfaces as a fomite (an inanimate object that can spread a disease. The article and graphs can be found here. Quick summary:
As an aerosol spray in the air - 3hrs
Copper surface - 4 hrs
Cardboard - 24 hrs
Stainless Steel - 48 hrs
Plastic - 72 hrs
The bigger the initial viral load, the more chances that one of those viruses
that got into your mouth or nasal passage, and are successful in finding an
un-cleaved ACE-2 receptor. The smaller the initial viral load, the more chances that
your immune system is able to identify the virus as an intruder, develop
antibodies against that specific virus in order to keep the virus in check.
Never giving it enough time and space to replicate itself.
2. Integrity and strength of your immune system
Your immune system has kept you alive until now. I won't pretend to know
anything about it, as I haven't researched it enough for this article. Suffice
it to say, that if you are treating your body well, by doing regular exercise,
hydrating, meditating, eating good wholesome foods, staying away from junk
foods, limiting your intake of both alcohol, caffiene and
recreational drugs, and taking certain key supplements, your immune system is
probably spectacular. And has a better than average chance against something
like Cov2 taking root in your body's cells. For the rest of us, if we don't
do all those things, our chances for getting through Covid-19 with no
symptoms lessen. Since the immune system is then having to battle diabetes
and obesity, dehydration, stress, poisons in our food, poisons in the smoke we
inhale and deal with the lack of key nutrients. And a new invading virus.
Update November 2026
You cannot change your age while isolating at home. But you can look after the body and immune system you have. Keep moving, get enough sleep, eat a varied, nutritious diet, maintain adequate hydration, avoid smoking and limit alcohol. Isolation can disrupt routines and increase stress, so staying connected with people matters too.
These habits support normal immune function and overall health. They cannot guarantee protection from severe COVID-19, but they give you practical things to do for yourself while reducing exposure to the virus.
3. Number of ACE-2 surface proteins
Dr. Klioz states that recent findings show that Advanced Age, Baseline health,
Physical Fitness and Diet are all risk factors associated with a severe
response to Covid-19.
He then reminds us that the two metabolically active hormones in the RAAS
system, Angiotensin-2 and Angiotensin 1-7 work in direct competition.
One raises blood pressure while the other one lowers it.
Furthermore, Angiotensin-2 not only raises blood pressure, but it also causes
inflammatory and atherogenic (induces plaques formation) responses in the
body while Angiotensin 1-7 lowers blood pressure and has anti-inflammatory and
antioxidant effects. He then postulates that:
"9:43 the dominant species (of either Angiotensin-2 or Angiotensin 1-7)
is probably determined by the individual's baseline health status"
Namely, Advanced Age, Baseline health, Physical Fitness and Diet. Makes
sense. Not confirmed. Just probably right based on what we've seen so far.
"9:48 in young healthy and physically fit individuals, Angiotensin 1-7 is
king. However in a sedentary, elderly individual with heart failure,
hypertension, diabetes, and a poor diet, Angiotensin-2 would rule."
So Dr. Klioz gives us a strong case for how to minimize the number of (membrane bound, un-cleaved) ACE-2
surface proteins. The places where COVID-19 gets into our cells and wreaks
havoc.
1. Stay young. Yeah, that's a tough one.
2. Baseline Health. Here's something we can all do.
3. Physical Fitness. Check.
4. Diet. For most of us, check.
3 outa 4 ain't bad.
Configuration of ACE-2 surface proteins
So what about the configuration of the ACE-2 receptor?
"10:03 in a situation where Angiotensin 1-7 is the dominant hormone, we would
expect Sheddase (ADAM17) to be working overtime, cleaving the external part of the ACE-2
metala-protein and thereby converting Angiotensin-2 to Angiotensin 1-7."
Never dawned on me. Of course, in this closed-loop feedback system the two
hormones are constantly vying for the right to be "King of the Blood
Pressure" hill. Even in a perfectly healthy individual with normal blood
pressure, as soon as someone drinks a glass of water or exerts themselves,
blood pressure goes up. The RAAS feedback loop gets Angiotensin 1-7 to lower
blood pressure. If the person gets dehydrated, the RAAS feedback loop gets
Angiotensin-2 to constrict the blood vessels and retain water to raise Blood
Pressure. Until they rehydrate.
"10:18 Let's assume the spike protein on the Sars/Cov2 viral particle,
specifically recognizes the intact transmural protein on our cell membranes. In
healthy individuals with an abundance of Angiotensin 1-7, most of the ACE-2
proteins would have been cleaved (by ADAM17) reducing the number of potential
viral gateways into our cells and limiting the chance of the cytoplasm reaching
that genetic critical mass."
Okay, at 10:38 in the video, I am watching a Covid-19 virus bounce off a
cleaved ACE-2 protein receptor. Going aha! That's what we've been
waiting for. So if you're body is in good balance, the
configuration of your ACE-2 receptors is very critical. While the rest
of the world would have your Blood Pressure go up due to many reasons already
cited, a young, healthy, physically active person on a "good" diet, and fully hydrated, more than likely has more cleaved ACE-2 receptors (which do NOT accept the
Covid-2) than fully "capped" ones, doing their best to keep blood
pressure down.
Update: September, 2021. Dr. Klioze was not far off in his video theory. The cleaved ACE-2 receptors (the tails) are useless for the virus to bind to, as shown above. They need an fully un-cleaved ACE-2 receptor to bind themselves to in order to breach the cell and start their infection and replication. What Dr. Klioze didn't postulate in his video, and Donato Zipeto et al do, is that the soluble ACE2 binds itself to both Angiotensin-II (to form Angiotensin 1-7) as well as the very S-protein spikes of COV2 viruses that happen to be passing by. Making those S-protein spikes useless and unavailable for binding with membrane bound ACE-2 receptors. Brilliant!
The virus is literally like a wolf amongst sheep. Some of the sheep
happen to have steel armor on them (the cleaved ACE-2 receptors). The other
ones, just the skin on their backs (the un-cleaved ACE-2 receptors). It hunts
for the easy openings, the un-cleaved ACE-2 receptors, having no chance to
get in via the cleaved ACE-2 proteins. In a chronically ill person, there
are more un-cleaved ACE-2 receptors, mostly due to the fact that Angiotensin-2
rules as the "King of the Blood Pressure Hill" and ADAM17 is not working to lower BP by cleaving membrance bound ACE-2.
Update October 2026
When I first wrote this, I wondered whether her blood pressure medicine had ironically saved her life by protecting her against severe COVID-19. I no longer have evidence to support that explanation. What became clear was the danger of continuing the same medications while she was barely drinking. Furosemide and spironolactone promote salt and water excretion. Ramipril lowers blood pressure and can compromise kidney filtration when circulating volume is depleted. Spironolactone and ramipril can also raise potassium, particularly when kidney function deteriorates. Medicines prescribed to help her had become hazardous under changed conditions.
The early studies suggesting people on these drugs did better were observational. Randomized trials (BRACE CORONA and REPLACE COVID) found no significant overall benefit from routinely stopping ACE inhibitors or ARBs in the patients studied. But BRACE CORONA excluded patients with clinical reasons to stop them, including hypotension, acute kidney injury or shock. Its findings therefore do not justify continuing these medicines during an emergency like Mom’s.
What the record shows is simpler. Three drugs that together either lowered her blood pressure, drained her fluids or raised her potassium, in a woman who had nearly stopped drinking. The hospital stopped all three, gave her fluids, and she recovered.
I went back to the research paper by Stookey and company, with new found knowledge, to see what changed in the months
between May and November 2020. Here is what I found.
"The hypothesized hydration effects suggest hypotheses regarding
strategies for COVID-19 risk reduction, such as public health
recommendations to increase intake of drinking water, hydration screening
alongside COVID-19 testing, and treatment tailored to the pre-infection
hydration condition. Hydration may link risk factors and pathways in a
unified mechanism for COVID-19 mortality. Attention to hydration holds
potential to reduce COVID-19 mortality and disparities via at least 5 pathways
simultaneously."
Same conclusions. Drink water. Keep the blood pressure normal, so that the RAAS
system is notifying ADAM17 to keep cleaving ACE-2 receptor proteins in order to create Angiotensin 1-7, in order to create sACE2 to bind with the S-protein spike on the COV2 virus and to leave in its cleaving wake, only an ACE2 tail on the cell membrane, giving the COV2 no easy targets. Or at least, fewer
of them.
"There is an urgent need for strategies to limit mortality from
coronavirus disease 2019 (COVID-19). Coronavirus is expected to infect up to
70% of the world’s population and kill millions of people. To date, the
main public health strategy for limiting mortality, to reduce exposure to the
virus via physical distancing, carries tremendous economic costs and
may create COVID-19 disparities, as not everyone can telecommute for work or
afford to shelter in place. The main treatment strategy for limiting
mortality involves ventilators, which may not be available and accessible in
adequate quantities. To address need for strategies that are less
costly, more equitable, and more accessible, this paper describes potential
causal paths from sub-optimal hydration before COVID-19 infection to
increased morbidity and mortality. The hypothesized mechanisms suggest
potential for free or low-cost, globally applicable drinking water
interventions and hydration-informed treatment (e.g. hypertonic resuscitation)
to limit COVID-19 mortality."
"Although not specified on the CDC’s list of risk factors, given the
ARDS literature (e.g. Rahmel et al.), a propensity to retain body water when
stressed or challenged is partially recognized as a risk factor for COVID-19
ARDS death. Recommendations for COVID-19 ARDS treatment explicitly aim to
achieve a negative fluid balance of 0.5–1.0 L/d. This paper
posits that attention to hydration may not only increase the success of
treatment for ARDS but may also prevent the development of ARDS and positive
fluid balance during COVID-19 infection, in the first place."
So they continue to reach the same conclusions that we saw in Mom. She has been
exposed to Covid. But rehydration potentially shut off the gateways for
infection.
Update November 2026: One case can't prove their hypothesis. Mom was infected, she was dehydrated, and she recovered after receiving fluids, medication withdrawal and treatment for dangerously high potassium. Her experience shows why adequate hydration assistance and prompt medication review matter when a resident stops drinking. Whether hydration before infection also reduces the risk of severe COVID-19 deserves a proper study.
Finally, their summary. I couldn't have said it better myself.
In sum, this paper hypothesizes that sub-optimal hydration in the
weeks prior to exposure to COVID-19 increases risk of COVID-19 mortality via
multiple possible pathways that favor fluid accumulation in the lungs. Evidence
from in-vitro, animal, clinical and epidemiological studies suggest that
chronic plasma hypertonicity, TBW deficit and/or hypovolemia may increase the
likelihood of COVID-19 infection, pre-set the body for exaggerated immune
response, increase tissue damage and leakage of fluid into the airway space,
and/or decrease capacity for active and passive transport of fluid out of the
airway space.Taken together,
the evidence suggests that strategies to limit COVID-19 mortality may need to
account for multiple determinants of water retention, fluid entry into and
fluid removal out of the lungs, simultaneously. The mechanism(s) described
above suggest testable hypotheses regarding screening to identify at-risk
groups, public health recommendations to limit risk, and clinical treatment
protocol. The pre-infection hydration condition is measurable by
biomarkers and modifiable by drinking water. The United Nations imperative to have drinking water
be available and accessible, worldwide, might be leveraged for COVID-19 risk
reduction. Attention to hydration by clinicians, researchers
and public health authorities has potential to block at least 5 pathways to
COVID morbidity and holds promise to prevent death due to COVID-19.
The implications of this for COVID-19 are massive.
The world can continue understaffing potential hot zones like nursing homes. And then wait for the residents to dehydrate or worse, have COVID-19 destroy their lung tissue to such an extent that they require ICU hospitalization, which for frail elderly patients carries a high risk of death. But why wait that long?
1. Remind everyone on the planet that getting water into themselves (hydrating) is an important key not only to surviving day to day, but especially during times of illness. And key to surviving a COVID-19 infection. To hydrate with an amount that is correct for your body weight and mass. For an 80kg relatively active person like myself, that happens to be about 3.7 litres of water (be it from drinking fluids or your food) every single day prior to being infected. To up that amount to 4 litres (or more) when doing strenuous activities OR if you are tested positive for COVID. And to continue at those levels until you are back to normal.
Update October 2026: The U.S. National Academies' general guideline is about 3.7 litres of total water a day for men and 2.7 litres for women, counting both drinks and food. Your needs go up with heat, exercise, fever and illness. If you test positive, make a point of keeping your fluids up until you're back to normal.
What are YOUR proper hydration levels? I wrote an article about some preliminary hydration research I did after I wrote this article. Find it here.
What about your electrolytes? All of that is fodder for another blog article. Stay tuned.
2. Overstaff all nursing homes in the world, with volunteers. To ensure hydration. It is too early to tell whether hydration will thwart COVID-19 from taking over the patients' respiratory systems. But it will definitely stop residents from dying from dehydration. And then we have the seniors on the same playing level as the rest of us. Hydrated. And far fewer of them would end up in hospital.
3. Ensure that every nursing home has the ability to properly monitor, report and react to blood pressure levels and fluid intakes.
4. That the nursing homes can administer IV therapy around the clock. So that residents never need hospitalization for dehydration. Or at worst, have ORT (Oral Rehydration Therapy) as a backup.
Update November 2026: Nursing homes need timely access to clinically supervised rehydration, including oral fluids when safe and IV therapy when indicated. Staff must recognize declining intake, arrange prompt assessment and medication review, and transfer residents to hospital when their needs exceed what the home can safely provide. Earlier intervention could prevent some dehydration emergencies and hospital transfers.
Update October 2026
5. Give every nursing home sick-day rules for residents on diuretics and blood pressure medication. When a resident stops eating or drinking, a nurse or doctor reviews those drugs the same day, before the resident ends up in an ambulance.
Remember, we are wearing masks and socially distancing ourselves to protect those most at risk. So far, judging by the mortality rates at nursing homes the world over, these two tactics alone are not working.
This is a fire that can be put out BEFORE it even starts. This is a fire that can be simply stopped by putting fire fighters at the scene of the crime - inside the nursing homes. There is no reason for letting the entire building be engulfed with flames and then send in the fire department to try to put it out. There is no reason NOT to tell the entire planet that hydration may be the key to this disease. At worst, we've kept the planet properly hydrated. At best, I'd rather not guess.
This article was not meant as a replacement for rigorous scientific method. I am entirely open to correcting my article as more people read it. If it gets the scientific community talking, awesome. If governments start including messages about hydration along with wearing masks and social distancing, fabulous. And if people pay a little more attention to hydration because of it, bravo.
In conclusion.
Rewritten October-November 2026. The original 2020 conclusion is preserved at the end of this post.
Mom almost died from being critically dehydrated. Not from Covid-19.
Three drugs she had taken for years, ramipril, spironolactone and Lasix (furosemide), each did their job on an ordinary day. When she was barely drinking, the two diuretics, furosemide and spironolactone, continued promoting salt and water loss. Ramipril could further lower her blood pressure and impair kidney filtration under those depleted conditions. Spironolactone and ramipril also increased the risk of potassium accumulating as her kidney function deteriorated. Nobody at the nursing home paused them.
She was saved by emergency hospital treatment. The team stopped those medications, treated her dangerously high potassium, and gave her intravenous fluids. Her prescribed IV rate was 100 mL an hour, equivalent to 2.4 litres over 24 hours if administered continuously.
When I first wrote this, I built an elaborate theory about ACE2 and ADAM17 to explain why she survived. The science since then hasn't supported it, and I've marked those passages above. What I'm left with is less exotic and, I think, more useful. During the outbreak, Mom was not getting the assistance she needed to keep eating and drinking. Her declining intake, combined with continued medication use, became an emergency. Hospital treatment brought her back.
Whether being well hydrated before infection lowers the risk of severe Covid is still an open question, and one that deserves a proper study. Whether elderly people on water pills and blood pressure drugs need someone watching their fluids and their meds when they get sick is not an open question. They do.
What can you do for yourself and your loved ones? Drink enough water, especially when you're sick. And if someone you love is on water pills or blood pressure medication and stops eating or drinking, call their doctor or pharmacist that same day and ask whether those drugs should be paused.
Mom’s story shows what is at stake when inadequate drinking assistance and a failure to reassess medications turn poor intake into an emergency.
Consolidated References (updated November 2026)
Dehydration, Covid and hydration
- Stookey JD, Allu PKR, Chabas D, Pearce D, Lang F. Hypotheses about sub-optimal hydration in the weeks before coronavirus disease (COVID-19) as a risk factor for dying from COVID-19. Medical Hypotheses. 2020;144:110237. doi:10.1016/j.mehy.2020.110237
- Institute of Medicine. Dietary Reference Intakes for Water, Potassium, Sodium, Chloride, and Sulfate. Washington, DC: National Academies Press; 2005. doi:10.17226/10925
- Manunta P, et al. Hypotension on admission and in-hospital outcomes in patients with COVID-19. Presented at: American Heart Association Hypertension 2020 Scientific Sessions; September 2020. (Conference presentation; the quoted figures come from news coverage of it.)
Sick-day rules
- Diabetes Canada Clinical Practice Guidelines Expert Committee. Sick-day medication list (SADMANS). In: Diabetes Canada 2018 Clinical Practice Guidelines for the Prevention and Management of Diabetes in Canada. Can J Diabetes. 2018;42(Suppl 1). Available at guidelines.diabetes.ca.
The renin-angiotensin system and ACE2
- Fountain JH, Kaur J, Lappin SL. Physiology, renin angiotensin system. In: StatPearls. Treasure Island, FL: StatPearls Publishing. NCBI Bookshelf ID: NBK470410.
- Zipeto D, Palmeira JF, Argañaraz GA, Argañaraz ER. ACE2/ADAM17/TMPRSS2 interplay may be the main risk factor for COVID-19. Front Immunol. 2020;11:576745. doi:10.3389/fimmu.2020.576745
Virus survival on surfaces
- van Doremalen N, Bushmaker T, Morris DH, et al. Aerosol and surface stability of SARS-CoV-2 as compared with SARS-CoV-1. N Engl J Med. 2020;382(16):1564–1567. doi:10.1056/NEJMc2004973
Blood pressure drugs and Covid
- van Vark LC, Bertrand ME, Akkerhuis KM, et al. Angiotensin-converting enzyme inhibitors reduce mortality in hypertension: a meta-analysis of randomized clinical trials of renin–angiotensin–aldosterone system inhibitors involving 158 998 patients. Eur Heart J. 2012;33(16):2088–2097. doi:10.1093/eurheartj/ehs075
- Wang Y, Tse G, Li G, Lip GYH, Liu T. ACE inhibitors and angiotensin II receptor blockers may have different impact on prognosis of COVID-19 [letter]. J Am Coll Cardiol. 2020;76(17):2041. doi:10.1016/j.jacc.2020.07.068 (Early observational data; superseded by the trials below.)
- Lopes RD, Macedo AVS, de Barros E Silva PGM, et al. Effect of discontinuing vs continuing angiotensin-converting enzyme inhibitors and angiotensin II receptor blockers on days alive and out of the hospital in patients admitted with COVID-19: a randomized clinical trial (BRACE CORONA). JAMA. 2021;325(3):254–264. doi:10.1001/jama.2020.25864
- Cohen JB, Hanff TC, William P, et al. Continuation versus discontinuation of renin–angiotensin system inhibitors in patients admitted to hospital with COVID-19: a prospective, randomised, open-label trial (REPLACE COVID). Lancet Respir Med. 2021;9(3):275–284. doi:10.1016/S2213-2600(20)30558-0
Sources and commentary from earlier versions
These are the sources and comments included as this article developed. Some explanations reflect my understanding at the time and have been corrected in the dated updates above.
Hydration
NutritionFacts.org The home base to Dr. Greger's amazing website. Not only has Dr. Greger amassed an amazing amount of information that will help you with Covid-19, if you are living with ANY chronic diseases, his information will change your life forever.
What the Corona
virus does to you
A lengthy article about how Covid works, with some great videos.
An informative short video on how viruses work. Only 1 thing missing in this video. They leave out the way that the virus gets in - via the ACE-2 receptor. Without that little tidbit of information, it makes it sound as if every cell in our body has no chance against this virus. It just walks in. Otherwise a decent video.
Renin Angiotensin
Aldosterone System
When blood
pressure drops (hypotension), kidneys sense this and they activate the RAAS
system. Which is supposed to assist in restoring blood pressure to normal pressure.
A good explanation of the RAAS system using doodling. Nice.
A great simple explanation of the RAAS system by a nurse. An excerpt from her video in explaining what the RAAS system
is all about:
“In response to low blood pressure, or Low serum sodium this system can kick
in to help compensate. When there is low sodium, there is low fluid volume.
Because where salt goes, water follows. If we don't have a lot of salt, we
don't have a lot of fluid. If you don't have a lot of fluid, your blood
pressure is going to be decreased. This system is in place to regulate blood
pressure by bringing it up, by this process of conversions and reactions.“
Blood Pressure -
drink a glass of water
A short article about how to alter your blood pressure using water
An article about water and dehydration
Dangers of
hypotension, dehydration and Covid 19
A possible link between low blood pressure, mortality and Covid-19
“Death is twice as likely in COVID-19 patients who
arrive at the hospital with mild low blood pressure, the study of nearly 400
people treated at an Italian hospital found.”
How do we get Low
Blood Pressure
This article talks about all the different ways you can get low blood pressure. I am only concentrating on the simplest one. Dehydration. They list 11 other ways of getting hypotension.
How Covid infects
cells via ACE2 receptors
Dr. Klioz’s explanation of how ACE-2 and Covid-19 work, the video
that I used to understand how RAAS and dehydration ties into Covid19 infection. Absolutely marvelous.
A great chalkboard explanation of the enzymes involved in RAAS and COVID-19 interaction.
The mechanics are a bit different from what Dr. Klioz suggests, but ultimately
the same holds true. RAAS system control is vital to keeping Covid-19
under control.
Types of
Intravenous Solutions and their different uses
A great video on the different types of fluids used in Intravenous solutions and why you would want to use different ones in different medical situations.
RAAS Inhibitors
and mortality in Hypertension
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3963752/
- written a while ago, talks about how RAAS inhibitors, hypertension (high
blood pressure) and mortality (death).
(Early observational study; superseded by the trials below.) ACE Inhibitors and Angiotensin II Receptor Blockers May Have Different Impact on Prognosis of COVID-19
Diabetes Canada. Sick-day medication guidance (SADMANS).
ACE2/ADAM17/TMPRSS2 Interplay May Be the Main Risk Factor for COVID-19
A great article hypothesis based on the latest knowledge of how ACE2, ADAM17 and TMPRSS2 all work together in the RAAS system. And the implications for COV2 infection.
Graphics References
Covid-19 Graphic - Photo by PIRO4D from Pixabay.
IV Therapy - Photo by Marcelo Leal on Unsplash
Hydration - Photo by Boxed Water Is Better on Unsplash
ADAM17 - Graphic by Donato Zipeto et al from their ADAM17 article.
Original conclusion (December 2020, superseded)
Ironically, while Ramipril, Spironolactone and Lasix (Furosemide) were slowly killing my mom by dehydrating her, Ramipril may have played a part in saving my mom's life. Ramipril is an ACE (Angiotensin Converting Enzyme) inhibitor. It stops Angiotensin I from being converted into Angiotensin II. By keeping Angiotensin II from being created, Ramipril potentially kept ADAM17 doing it's PROTECTIVE work. It appears that the result was that ADAM17 continued to cleave ACE-2 receptors, in order to create Angiotensin 1-7 and it continued to create a soluble ACE2 that would both bind to the Spike Proteins on the virus rendering them unable to bind to membrane bound ACE2, while leaving behind ACE-2 tails that the COV2 virus could not bind to and potentially infect the person.
Mom almost died from being critically dehydrated. Not from Covid-19.
She was saved by removing her from all her meds, clearing out the excess potassium and getting vital fluids (water) and electrolytes back into her. Upwards of 2.4L of IV fluids a day (100cc an hour). For a sedentary person, to cure her of her dehydration and take her off Ramipril (Hypertensive med) and Lasix (Chronic Heart Failure med).
She was initially suffering from high blood pressure, which was why she was on Ramipril. However, as you have read in this article, one of the reasons for high blood pressure is caused by our body's trying to self regulate a very simple problem - lack of water. The body winds up creating Angiotensin II which binds to receptors in our cells that cause our blood vessels to vasoconstrict. If we don't treat the root of the problem (lack of water), that message from command control (the kidneys) keeps coming. And in its wake, it causes ADAM17 to work its harmful effects. Once the kidneys have enough blood flow (because we rehydrated), ADAM17 eventually gets the message to lower blood pressure. It then cleaves ACE2 receptors creating soluble ACE2 which then does double duty, converting any Angiotensin II to Angiotensin 1-7. Thereby reversing the vasoconstriction and vasodilating our blood vessels thereby lowering blood pressure. And binding to any available S protein spikes on free floating viruses in the area. While making the membrane ACE2 receptor a non-target for COV2 with only a cleaved tail left behind.
In a lot of older, stressed, chronically dehydrated individuals, blood pressure is a constant challenge. These people don't get enough water. The creation of Angiotensin II is supposed to be a fine tuning mechanism in humans. Missing a bit of water and hence your blood pressure is low? No problem, the kidney sends out the message, to vasoconstrict blood vessels with Angiotensin II. But after you drink that glass or two of water, the kidney’s give the A-OK signal by stopping the production of Angiotensin II. ADAM17 cleaves the ACE-2 receptors, creating a soluble form of ACE2 that binds with the excess Angiotensin II, which is converted to Angiotensin 1-7 and the blood vessels relax. Blood pressure goes down. Extra soluble ACE2 then binds to the S protein spikes of viruses making them inert at the same time. Leaving behind cleaved ACE2 tails in the cell membrane that are useless for viruses to bind to.
In chronically dehydrated individuals, this vasoconstriction request is on all the time. The body is flooded with Angiotensin II. ADAM17 never gets the message to cleave ACE2 receptors! These people don't have a high blood pressure problem. They are simply dehydrated. ADAM17 appears to be like an on/off switch. ADAM17 is either raising BP or lowering it, by its actions as reported by Donato Zipeto et al. If you are chronically dehydrated, ADAM17 is stuck in its harmful cycle. The ACE2 receptors just lay there, like sitting ducks, until the COV-2 virus comes along and sees them un-cleaved. Because ADAM17 never got the message to cleave them. And then, just like a wolf, the virus does what its supposed to do.
It takes out the weakest among us. The ones that haven't been hydrating properly.
What can you do at home, for yourself and your loved ones? You can't self administer Ramipril. But you can ensure that you keep properly hydrated through eating and/or drinking enough water. It does work.
Mom is living proof.